Neurology-Led Care in Gangdong-gu, Seoul · 1:1 Specialist Consultation
en-US

Autonomic Testing: The Symptom List That Sends You There
Dizziness, palpitations, chronic bowel change and unexplained insomnia can share one cause. Seoulhoho Hospital publishes who it considers for autonomic testing.
Autonomic Testing: The Symptom List That Sends You There
Medically reviewed by Dr. Ho-Sang Yoon, Representative Director and Chief Neurologist, Seoulhoho Hospital
Some patients arrive at a neurology clinic having already been to four other specialties. A cardiologist looked at the palpitations. A gastroenterologist looked at the bowel. Someone else looked at the insomnia. Each found little, and nobody looked at all of them together.
That pattern is what the autonomic nervous system service exists for, and Seoulhoho Hospital's published candidate list reads like a description of it.
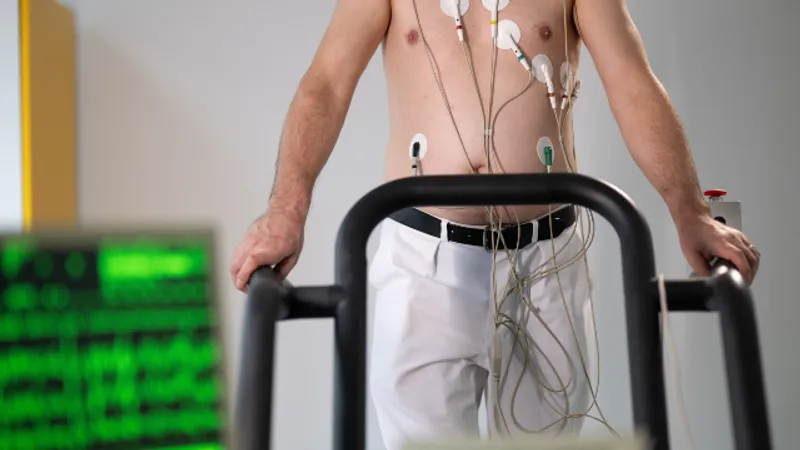
The list, as published
The clinic identifies people who frequently experience the following as candidates for autonomic function testing:
- dizziness
- palpitations
- headaches
- chronic constipation or diarrhea
- unexplained anxiety, depression or insomnia
- numbness in the hands and feet, in association with diabetes or hypertension
Read that as six separate complaints and it looks like a list of unrelated problems. Read it as one list and the logic appears: these are the outputs of a system that regulates things nobody chooses to regulate.
The clinic describes that system directly — the autonomic nervous system operates involuntarily and regulates functions such as breathing, digestion and circulation, and dysfunction can affect blood pressure, heart rate, digestion, bladder function, sweating and temperature regulation.
The National Library of Medicine's overview of autonomic nervous system disorders covers the general territory in patient language.
Why this gets missed
Because every item on that list has a more common explanation, and each specialty reasonably investigates its own.
Palpitations go to cardiology. Bowel changes go to gastroenterology. Insomnia goes to sleep medicine or to psychiatry. Dizziness goes to ear, nose and throat, or to neurology. Each investigation is appropriate; each is also partial.
What the published list does is name the case where the combination is the finding. Not any one symptom, but several of them in the same person, persisting, without a single-organ explanation.
If you recognize yourself in three or more of those six entries, that recognition is the referral.
What the testing involves
The clinic's published sequence is five steps: consultation to review symptoms and medical history; evaluation of possible neurological and autonomic causes; testing, performed when appropriate; treatment planning according to the patient's condition; and follow-up to monitor symptoms and treatment response.
Its broader diagnostic services are described as including blood tests, cerebral blood-flow and carotid ultrasound, and other neurological testing, with autonomic function testing specifically used for autonomic evaluation.
Note step three: testing is performed when appropriate, which means the consultation decides whether it happens rather than the booking doing so.
What the clinic says treatment can and cannot do
The published position is carefully bounded, and the boundary is stated twice.
The treatment approach is described as intended to address autonomic imbalance and related symptoms, with outcomes varying according to the underlying cause and individual response — and the clinic adds, in its own words, that treatment should not be presented as guaranteeing a cure.
Its approved statement is similarly modest: the treatment is intended to evaluate and manage symptoms associated with autonomic nervous system dysfunction, and the specific approach and suitability are determined by the physician based on the patient's symptoms and condition.
A clinic writing "should not be presented as guaranteeing a cure" into its own material is unusual, and it is the sentence to remember if you encounter a more confident claim elsewhere.
The six-week program, and what it means for a visitor
This is the practical heart of the article for anyone traveling.
The clinic's autonomic dysfunction program is described as autonomic function testing followed by injection treatment and intravenous treatment, with an intravenous course listed once weekly for 6 weeks, depending on whether sympathetic or parasympathetic activity is elevated.
Six weekly sessions is a six-week commitment. For a resident that is an inconvenience; for a visitor it is the entire trip, and then some.
So the question to settle before booking is not whether the program exists but which parts of it apply to you and which can happen where you live. The evaluation and the testing are a short engagement. A six-week weekly course is not, and nobody should discover that distinction after arriving.
The clinic does not publish a fixed number of visits for the autonomic disorder service generally — only the six-week figure for that specific program — which makes this a question rather than a lookup.
Risks and preparation
The published risk note is brief and honest: risks depend on the specific diagnostic test, medication or treatment used. There is no single risk profile because there is no single procedure.
Preparation is likewise conditional: it depends on the examination or treatment selected, with the clinic recommending that patients prepare information about symptoms, medications and supplements, and relevant medical history for autonomic neuropathy evaluation.
That request for supplements alongside medications is worth taking literally. Things that affect heart rate, blood pressure, sleep and bowel function are widely available without prescription, and they belong on the list. The National Library of Medicine's overviews of dietary supplements and drug safety cover why.
Who is not suitable
Three groups, as published: patients whose symptoms are caused by an unrelated condition; those who require urgent emergency care; and those whose medical condition requires a different type of specialist evaluation.
The first of those is the reason the evaluation exists rather than an argument against it — establishing whether the symptoms share a cause is precisely what is being assessed.
The second matters for a symptom list that includes palpitations and dizziness. Chest pain, fainting, or a sudden change rather than a chronic pattern belongs in urgent care, not in a scheduled appointment. The National Library of Medicine's emergency medical services page covers the general position.
Preparing the one document that matters
Because the finding here is a pattern rather than a single symptom, the useful preparation is a record that shows the pattern.
A symptom-by-symptom list with, for each: when it started, how often it happens, what brings it on, and how long it lasts.
A note of what has already been investigated and by which specialty, with results. This is what stops the sixth investigation repeating the first five.
Blood pressure and pulse readings taken lying and then standing, over several days, if you can. The clinic's published diagnostic vocabulary includes orthostatic assessment, and a home record of what happens when you stand up is information nobody else can collect.
Everything you take, prescription and otherwise.
The clinic's consultation enquiry route is the published channel for sending it, and the clinic states that the physician sees patients personally in a one-to-one consultation.
Setting expectations honestly
Three things worth holding in mind before an autonomic evaluation.
A named cause is not guaranteed. The published position is that the specific approach and suitability are determined by the physician based on symptoms and condition, and that outcomes vary with the underlying cause.
Management, not cure, is the stated frame. The clinic says so itself.
The useful output may be a reframing. For a patient who has been investigated organ by organ, being told that several symptoms may share a mechanism is itself a result — it changes what is monitored and who monitors it, even before any treatment starts.
The clinic's account of how it approaches care describes the assessment sequence that reframing would come from.
The instinct that makes this hard to diagnose
Worth naming, because it explains the four-specialties pattern from the patient's side as well as the clinician's.
Patients present their most alarming symptom. Somebody with palpitations, chronic bowel change, dizziness and poor sleep will lead with the palpitations, because a racing heart is frightening in a way an irregular bowel is not. The consultation then addresses the heart, reasonably and thoroughly.
The other three symptoms go unmentioned, or get mentioned in passing and filed as unrelated. From the clinician's side there is nothing wrong with the reasoning — they were told about one problem and they investigated it.
Which means the pattern only appears if the patient presents it as a pattern. That is not a natural way to describe how you feel, and nobody teaches it.
The correction is mechanical rather than clever: write the list before the appointment, include everything even where it seems irrelevant, and hand it over as a list rather than answering questions one at a time. If several items on the published six appear, say so explicitly.
What "sympathetic or parasympathetic" is doing in the published record
The clinic's description of its program notes that the intravenous treatment differs depending on whether sympathetic or parasympathetic activity is elevated.
That detail is worth understanding at a plain level, because it explains why the testing precedes the treatment rather than accompanying it.
The autonomic system has two branches that work in opposition — broadly, one that mobilizes the body and one that settles it. Symptoms can arise from either being over-represented relative to the other, and the resulting complaints can look similar from outside while calling for different responses.
So an evaluation that measured nothing and treated everyone the same would be guessing at which branch was involved. The published sequence puts testing first for that reason, and the treatment that follows is described as selected according to the finding.
That is the clearest available argument for why this should not be approached as a package to book, and why the clinic describes suitability and approach as determined by the physician.
What to do with a negative result
A situation worth preparing for, because it is a likely outcome and patients handle it badly.
If testing does not identify autonomic dysfunction, that is information rather than a dead end. It removes a possibility that had been open, and it redirects the search.
The published exclusion list anticipates this: patients whose symptoms are caused by an unrelated condition are among those for whom this treatment may not be suitable. Establishing that is part of what the evaluation is for.
The useful question at that point is not "what else can we try here" but "what does this result rule out, and where would you look next?" An assessment that narrows the field has done something, even when the thing it found was an absence.
The Bottom Line
- Six symptoms are named as candidates for testing: dizziness, palpitations, headaches, chronic constipation or diarrhea, unexplained anxiety, depression or insomnia, and numbness in the hands and feet with diabetes or hypertension.
- The combination is the finding, which is why these symptoms are routinely investigated separately by different specialties and the pattern goes unnoticed.
- The clinic writes its own limit into its material: treatment should not be presented as guaranteeing a cure, and outcomes vary with cause and individual response.
- One program is published as once weekly for 6 weeks, which is a residency rather than a trip — settle which parts apply to you before booking.
- Bring a pattern, not a complaint: dated symptom records, what has already been investigated, home blood pressure and pulse readings lying and standing, and every medication and supplement.
Frequently Asked Questions
Who does the clinic consider for autonomic function testing?
People who frequently experience dizziness, palpitations, headaches, chronic constipation or diarrhea, unexplained anxiety, depression or insomnia, or numbness in the hands and feet in association with diabetes or hypertension.
What does the autonomic nervous system do?
The clinic describes it as operating involuntarily and regulating functions such as breathing, digestion and circulation, with dysfunction able to affect blood pressure, heart rate, digestion, bladder function, sweating and temperature regulation.
Will I definitely have testing?
Not necessarily. The published sequence performs testing when appropriate, after the consultation and evaluation of possible causes.
Can this be cured?
The clinic states that outcomes vary according to the underlying cause and individual response and that treatment should not be presented as guaranteeing a cure. The stated frame is evaluation and management.
How long is the treatment program?
One published program is described as autonomic function testing followed by injection and intravenous treatment, with an intravenous course listed once weekly for 6 weeks depending on which branch of the system is more active.
Can a visitor complete that program?
Six weekly sessions is a six-week commitment. Establish before booking which parts apply to you and which could be done where you live.
What should I prepare?
A dated record of each symptom, a note of what has already been investigated and by whom, home blood pressure and pulse readings taken lying and standing, and a complete list of medications and supplements.
When should I seek urgent care instead?
The published exclusions include patients requiring urgent emergency care. Chest pain, fainting or a sudden change rather than a chronic pattern belongs in urgent care.
This article is for general informational purposes and does not constitute individualized medical advice. It is not a self-diagnosis tool. The symptoms described have many possible causes, most of them unrelated to the autonomic nervous system, and recognizing yourself in a list is not a diagnosis. Only a qualified neurologist who has examined you and reviewed your history can determine whether this evaluation is appropriate.